Importance of Data Collection in Healthcare: An Overview
Most healthcare data already exists. It was recorded to treat a patient, bill for that treatment, or run a service, and almost none of it was recorded in order to answer a research question. That gap is where the importance of data collection actually lies, and it is the part most accounts skip.
- Why data collected for care and data collected for research are different material
- What reporting standards require you to disclose about where your data came from
- Which decisions are fixed at collection and cannot be repaired by analysis
- “More data is better data.” Volume and fitness for purpose are separate properties. A large dataset built for billing can answer fewer clinical questions than a small one built for the question being asked.
What this article covers
This article is about why data collection matters, rather than how it is done, and it takes one distinction seriously: the difference between data gathered to care for a patient and data gathered to answer a question. Those two activities produce different material, and the material fails in different ways.
Most of what goes wrong in a healthcare study is settled before any analysis starts. A variable was not recorded, or a code meant something other than the analyst assumed, or an outcome was measured on a scale no other study used. None of those can be repaired once the data are in hand.
Three companion articles cover the neighbouring ground, and this one does not repeat them. The tools and technologies are covered in medical data collection: challenges, strategies and future impacts. Which organisations hold healthcare data is covered in significant medical data collection sources. The individual methods are covered in methods and techniques of data collection in health care research.
What none of them covers is the distinction this article turns on. That gap is the reason for it.
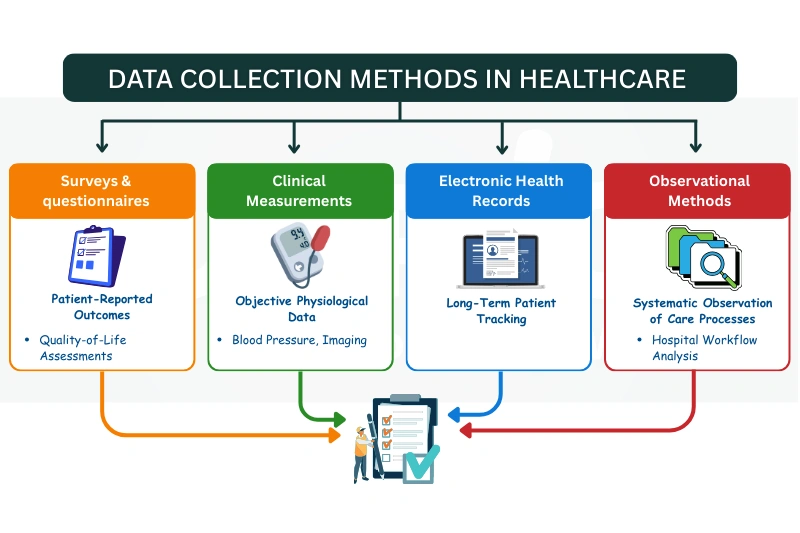
Two kinds of healthcare data
Healthcare data divides by provenance rather than by subject. The question is not what the data describe, but what someone was trying to achieve when they wrote it down.
Primary data are collected to answer a specific question. A trial measures the outcome its protocol specifies, and a survey asks what the researchers decided to ask. The question comes first, and the collection is then designed backwards from it.
Secondary data, often called routinely collected data, already exist for some other reason. Electronic health records exist so that clinicians can treat patients, claims data exist so that someone can be paid, and registries exist for surveillance or audit. Research use is a later idea, and the data were never shaped by it.
| Collected for research | Collected for care or administration | |
|---|---|---|
| Designed by | The question | The workflow, the billing code, the form |
| Variables present | Whatever the protocol specified | Whatever the work required |
| Definitions | Fixed in advance and documented | Local, and often undocumented |
| Missingness | A known problem, usually counted | Often invisible, and rarely random |
| Population | Defined by eligibility criteria | Defined by who happened to attend |
| Cost | High, and paid up front | Low, because someone else paid it |
| Scale | Limited by that cost | Very large |
The last two rows explain why routinely collected data are so attractive, which is that they are enormous and cheap. The rows above them explain why that bargain carries a price.
This is not an argument that primary data are superior, because many questions cannot be answered any other way than from routine data. Rare outcomes, long follow-up and whole populations all lie beyond the reach of a funded study.
The argument is narrower than that. A dataset inherits the purpose it was built for, and that purpose decides which questions it can answer honestly. Establishing which of the two you are holding is the first analytical decision rather than an administrative detail.
Figures: from patient to dataset
Figure 1 traces the filters that stand between a patient and the data a study receives. Figure 2 separates the decisions that are fixed at the point of collection from those that can still be changed. Together they help authors plan data collection so that the dataset can answer the study question, and describe its limitations accurately.
Every step between the patient and the dataset is a filter. Each one was applied for a reason, and none of those reasons was your study.
What to look for. The narrowing is the point, and so is the reason for it. None of these filters is a mistake. A clinician who does not record a normal finding is working correctly, and a coding system that lacks a term for an unusual presentation is doing what coding systems do. The losses are rational at every step and they are still losses by the time the data reach you.
Schematic. Bar widths illustrate successive narrowing and are not drawn from measured data.
The asymmetry matters more than any individual item. Everything on the left is permanent by the time the data exist.
What to look for. The right column is where almost all methodological attention goes, and it is the column that can be revisited. The left column is settled once and then governs everything afterwards. That is the practical case for spending effort on collection, and it is why a study protocol that specifies the analysis in detail and the data sources in a sentence has its proportions the wrong way round.
Schematic. Handling of missing values appears on the right because the method is a later choice; the reason a value is missing was settled at collection.
Data collected for care was collected for something else
There is a reporting guideline for studies that use routine health data, and its opening definition is the clearest statement of the problem. RECORD describes such data as “data collected without specific a priori research questions developed prior to utilization for research”.1 It names the purposes they were collected for instead: “administrative and clinical purposes without specific a priori research goals”.1
The consequence is stated just as plainly. “The rationale underlying routine data collection may affect the quality and applicability of the data”.1 That sentence is the whole argument of this article, compressed.
Codes move with the incentive, not with the patient
The sharpest illustration is financial. RECORD warns that “administrative data are particularly subject to errors in upcoding or opportunistic coding”.1 It explains the mechanism directly: hospitals “may maximize reimbursement by liberally applying more complex disease codes”, and this happens “when hospital reimbursement is based on complexity of the case mix”.1
Pressure also runs the other way. Some codes “may be avoided because of patient stigmatization or provider penalties”.1 A diagnosis can therefore be under-recorded for reasons that have nothing to do with how often it occurs.
Coding behaviour is not stable over time or across places. RECORD notes that “the introduction of provider billing incentive codes may change the likelihood of a code being used over time”.1 It adds that “codes may function differently in different populations or databases”.1
A rising count of a diagnosis may therefore mean more disease, or more coding of the same disease. The data alone cannot distinguish the two. Anyone presenting a trend from administrative data has to say which they think it is, and why.
Why collection outranks analysis
The methodological literature puts the same point in terms of effort. One review of data collection theory describes it as “the process of data collection, which is often neglected but it could be more important than both the data and the analysis”.2 The reasoning is that “quality of data collection strongly contributes to quality and trustworthiness of the results”, and that “poor-quality data entry often leads to unreliable data output”.2
The same review makes a point that electronic records do not solve on their own. “Even if the information is electronic, there is no guarantee that has been inputted in the proper location.”2
What a paper therefore has to disclose
RECORD exists because this information was routinely missing from published studies. Its requirements are concrete, and they are worth reading as a list of what a reader needs in order to trust a result.
- How subjects were identified. “The methods used to identify study subjects should be explicitly and clearly stated”.1
- The codes themselves. RECORD asks for “a complete list of codes and algorithms used to classify exposures, outcomes, confounders, and effect modifiers”.1
- What cleaning was done. “Authors should provide information on the data cleaning methods used in the study”, including how they “screen for erroneous and missing data”.1
- Whether datasets were joined. Authors must “state whether the study included person-level, institutional-level, or other data linkage across two or more databases”, and “linkage techniques and methods used to evaluate linkage quality should be provided”.1
RECORD also sets out why it asks. Reporting these things lets a reader “assess its internal and external validity”, and it is “critical to permit the reader to assess the impact of any linkage error”.1 On missing values the guideline is blunt. “Missing data are problematic for all observational research”, and “missing data can result in selection bias”.1
One caution about validity is worth carrying forward into the next section. RECORD notes “the risk of misclassification bias in studies using routine health data”, and that “validation of identification methods has been increasingly emphasized as essential”.1
What collection decides that analysis cannot undo
It would be easy to turn the previous section into a general verdict on routine data. The evidence does not support one. What it supports is a claim about variability, and variability is the more useful finding because it tells you where to look.
The collection method changes the answer
One study compared ways of capturing the same two variables across the same admissions. Inpatient medical record review was the reference standard. Manual collection from ward-based sources “captured only 376 (69%) of the 542 in-patient episodes”.3
Electronic administrative data did far better. They “had the highest levels of agreement” with record review, “for both length of stay (93.4%) and discharge destination (91%) data”.3 These are percent agreement figures, and the study reports no chance-corrected statistic.
Nothing about the patients differed between those two columns. Only the method of capture did.
The reference standard changes the answer too
A validation study of type 2 diabetes recording shows how much the comparison itself matters. Against physician re-diagnosis the database looked excellent, with “all estimates… above 90%” except on one comparison.5 That exception was sensitivity against paper records, which fell to “54%; 95% CI 47% to 61%”.5
The reason sits in the paper records themselves. “Only 190 of 437 (43.0%)” patients had paper-based medical records at all, and of those, “87 (46%) did not have any records for type 2 diabetes mellitus in their medical charts”.5 The condition was nonetheless confirmed in every case examined.5
One database produced two very different verdicts. The difference lay entirely in what it was measured against.
Validity is condition-specific, not global
A systematic review of European electronic health records examined how well recorded cardiovascular diagnoses matched reality. Its figures vary sharply by condition, and the variation is the finding.
| Diagnosis | Positive predictive value | Sensitivity |
|---|---|---|
| Myocardial infarction | “≥ 80% in… 88% of myocardial infarction” studies | “≥ 80% for 91% of myocardial infarction studies” |
| Stroke, all | “≥ 80% in… 70% of stroke studies” | “≥ 70% for 73% of stroke studies” |
| Stroke, ischaemic | “≥ 80% for 80% of ischaemic stroke” | not reported separately |
| Stroke, haemorrhagic | “only 44%” of studies reached ≥ 80% | not reported separately |
| Heart failure | “≥ 80% in 74% of heart failure” studies | “≤ 66% in all but one heart failure study” |
Two readings follow. A myocardial infarction recorded in these databases is usually a real one, and most real ones are captured. Heart failure is different: when the code is present it is usually right, but most cases are missed.
The review reports “considerable heterogeneity (I2 > 75%) between sensitivity and PPV estimates for all diagnoses”, and notes that “few studies reported specificity or negative predictive value estimates”.4 Its own conclusion is not that these data are unusable. It is that validity has to be established for the specific diagnosis, in the specific database.
Before relying on a coded field, look for a validation study of that code, in that database, for that population. If one exists, its figures belong in your methods. If none exists, that absence is itself a limitation worth stating.
This is what RECORD means by emphasising that “validation of identification methods has been increasingly emphasized as essential”.1
Completeness, and why values go missing
A longitudinal study of surgical records puts the problem in order of severity. “Incompleteness is assumed as the most significant threat to data usability.”6 The authors add that “the reasons for incompleteness of these data are not fully understood yet”, and that “improvements in completeness are not consistent across different empirical studies”.6
Two of the reasons they give explain why absence is not random. Clinical staff “experience too heavy workload to document the same information in different places”, and “emergencies tend to be less complete documented”.6 Missingness therefore tracks workload and acuity, which are often the very things under study.
Their measured effect is real but modest. Across 659 records, mean completeness scored 6.02 out of 10 for paper records and 7.2 for electronic ones.6 Moving to an electronic system improved completeness. It did not solve it, and the authors warn that incompleteness “poses a major risk to utilizing the described data for secondary purposes”.6
Coding accuracy is a separate question from completeness. One single-site audit found the “primary diagnosis was incorrectly coded in 57 (26 per cent) records” and the “secondary diagnosis was incorrectly coded in 21 (9.9 per cent) records”.7 That study is one hospital, and its own text gives the primary figure inconsistently, so it is worth treating as indicative rather than as a rate to quote.
The decision that forecloses synthesis
The most consequential collection decision is often the quietest one: how to measure the outcome. It rarely feels like a decision at all.
The COMET Handbook sets out what follows from it. “Inconsistencies in outcomes have caused problems for people trying to use health care research”, because “variability in how outcomes are defined and measured can make it difficult, or impossible, to synthesise”.8 Where “outcome definitions may vary widely between investigators”, the result is work that “made it extremely difficult to compare and combine in meta-analyses”.8
The scale of the problem has been counted. A review of 132 core outcome set development studies found a median of 82 unique outcomes per condition, with a range from 12 to 5,776.9 The upper end is not a typographical error: the review reports that “Chong et al. in a systematic review on pediatric chronic kidney disease reported 5,776 different outcomes from 213 studies”.9
Definitions diverge as well as measures. “Varying definitions for the same outcome across included trials were reported in 53 studies (52.0%).”9 The authors state the consequence directly: this “impacts negatively on evidence synthesis thereby contributing to research waste”.9
A core outcome set is “an agreed standardised collection of outcomes which should be measured and reported, as a minimum” in trials of a given condition.8 It is a floor rather than a ceiling, and it does not stop anyone measuring more.
A minimum dataset does the equivalent job for study design, serving as “a framework which can be used for the purposes of study design and appraisal of studies”.2
Both work only if they are consulted before collection. Afterwards they become a list of what is missing.
One further warning from the same handbook belongs here, because it concerns what happens after collection. “Empirical evidence shows that outcomes that are statistically significant are more likely to be fully reported”, and selective reporting means “fully informed decisions cannot be made about the care of patients”.8 Collecting an outcome and not reporting it is a different failure from never collecting it, and an agreed list guards against both.
Reuse, consent and governance
If routine data are to be used for research, someone has to decide whether that is permitted and on what terms. This is not a formality bolted on at the end, because the answer can determine whether the study is possible at all.
The World Health Organization published a policy on exactly this question, which “covers the reuse of health data for research purposes”.11 Its scope is narrower than it might appear. It binds WHO staff and WHO-funded researchers, so it is a statement of principle elsewhere rather than a regulation.
Its starting position favours sharing. The policy holds that “the sharing of health data is a global public good”, and that researchers “must share data for further research where possible”.11 The first question it asks is nonetheless about permission: “has participant or patient consent been given for reuse”.11
Consent is not treated as a veto. The policy states that an absent or ambiguous consent “should not preclude sharing of research data”, where “the research has important social value” and the arrangements “balance and protect the privacy of individuals and the dignity of communities”.11
The policy distinguishes them carefully. De-identification is “the process by which those variables that can identify an individual are irreversibly removed”.11 In the weaker case the identifying variables “are masked in some way or replaced by a code that has a key”.11 A key that exists can be used, so the two states carry different risk.
One sentence in that policy deserves more attention than it usually gets: “there are no global standards for anonymization or de-identification”.11 A dataset described as anonymised has been anonymised to someone’s standard, and the paper should say whose.
The governance mechanisms the policy names are practical rather than abstract. They include arrangements to “employ data use agreements”, to “maintain appropriate user agreements”, and to “appoint an independent panel that includes members of the public to review data requests”.11
Why standardisation and governance arrive together
Combining records across institutions raises both problems at once. A study of a common data model describes the technical half as the “conversion of vast amounts of complex, and heterogeneous EMR data into a standardised structured data model”, in order to provide “a common platform for analysing EMR data across diverse healthcare settings”.10
The obstacle is the shape of the source systems. The authors describe “the inherent complexity of EMR databases”, with “thousands of proprietary tables” and “the heterogeneity of each institution’s EMR schema”.10 None of that structure was designed for cross-site analysis, because it was designed to run a hospital.
They are equally direct about the non-technical obstacle: “concern over data sharing and privacy breaches and lack of clarity over governance and consent”.10 Their answer keeps the data where they are. Each site’s data “is securely firewalled within its respective local site”, and “collaborative analyses are always conducted within each institution’s firewalled network”.10
Collection practice varies, and that is a governance problem too
Variation in how a field is collected can defeat analysis as effectively as missing it altogether. A National Academies report on one class of data found that “the categories collected vary by hospital, and hospitals obtain the information in various ways”, and that “the data do not flow among these entities in a cohesive or standardized way”.12
That report concerns race, ethnicity and language data in United States hospitals, and its findings should not be generalised beyond that. Within that scope it records two consequences worth noting. Merging sources can mean “overriding high-quality data with poor-quality data”, which reduces “the value for analytic processes”, and it “raises the possibility that conflicting data may, in some instances, be assigned to a single individual”.12
It also found that collection alone changes nothing. “Fewer than one in five hospitals that collected these data used them for any of these purposes.”12 Data gathered and never used is a cost without a return, and it is the one failure mode this article has not otherwise covered.
Common mistakes
| Mistake | Stage | What it costs | What to do instead |
|---|---|---|---|
| Treating a database as a dataset | Before analysis | Variables are interpreted as though they were collected for the question being asked | Establish what each field was recorded for, and by whom |
| Assuming a code means its label | Before analysis | Misclassification that no statistical method will reveal | Look for a validation study of that code in that setting |
| Treating missing values as random | Analysis | Bias in a direction nobody has estimated | Ask why the value is absent before deciding how to handle it |
| Choosing an outcome measure in isolation | Design | Results that cannot be pooled with anything else | Check whether a core outcome set exists for the condition |
| Deciding variables are optional to save effort | Design | A confounder that cannot be adjusted for, permanently | Collect what the analysis plan requires, and nothing it does not |
| Leaving provenance out of the write-up | Reporting | A reader cannot judge whether the data support the claim | Report the source, the cleaning and the linkage as methods |
| Assuming scale compensates for fitness | Throughout | A very precise estimate of the wrong quantity | Judge the dataset by its purpose, not by its row count |
The importance of data collection is not that healthcare generates a great deal of it. The importance is that collection fixes what any later analysis can establish. Data recorded to treat a patient carry the shape of that purpose. They answer research questions only where the two purposes happen to coincide. Establish which of the two kinds of data you are holding before deciding what it can show. Then record where it came from, so a reader can judge the same thing.
How to apply this to your work
- Write the question down first, and only then ask which data could answer it.
- Establish the provenance of every source, including what it was originally collected for.
- List the variables the analysis requires, and check that each one exists and means what you assume.
- Look for a validation study of any code or derived field you intend to rely on.
- Check for a core outcome set before choosing how to measure the outcome.
- Plan for missing data by asking why values would be absent, not only how many are.
- Settle the governance for reuse before the data move, not afterwards.
- Record the provenance in the methods, including cleaning, coding and any linkage.
Common questions
What is data collection in healthcare?
It is the recording of information about patients, services and populations. It covers two distinct activities that are often treated as one. The first is recording information in order to deliver and administer care. The second is gathering information in order to answer a defined question. The two produce different material, and most of this article is about that difference.
Why is data collection important in healthcare?
Because collection sets the ceiling on what analysis can establish. A variable that was never recorded cannot be recovered. A definition that varied between sites cannot be made consistent afterwards. An outcome measured on an unusual scale cannot be pooled with anything else. Those failures are decided at collection and are permanent by the time anyone looks at the data.
What is the difference between primary and secondary data?
Primary data are collected to answer the question being asked, so the question shapes what is recorded. Secondary data already exist for some other purpose, such as treating patients, billing, or audit, and research use is a later idea. The practical consequence is that secondary data carry the shape of their original purpose into every analysis that uses them.
Can electronic health records be used for research?
Yes, and for some questions they are the only practical source. They cover whole populations, long periods and rare events that no funded study could reach. The condition is that they were built to support care rather than to answer questions. What is present, what is missing, and what each field means all follow from clinical workflow rather than from a protocol.
Does more data mean better evidence?
No. Volume and fitness for purpose are separate properties, and scale does not repair a mismatch between what was recorded and what is being asked. A very large dataset produces a very precise estimate. That is useful only if the estimated quantity is the one the question is about.
What should a paper report about where its data came from?
Enough for a reader to judge whether the data support the claim. That means the source and the population it covers. It also means what the data were originally collected for, how variables were defined and coded, what cleaning was applied, and how any datasets were linked. Reporting standards exist for studies using routinely collected data, and they exist because this information was routinely absent.
Why does missing data matter so much?
Because in routinely collected data it is rarely random. A test result is usually absent because nobody ordered the test, and the decision not to order it was clinical. Absence therefore carries information about the patient. Discarding incomplete records and filling them in can each introduce bias rather than remove it.
What is a minimum dataset or core outcome set?
Both are agreed lists that constrain what gets collected or reported. A minimum dataset specifies the variables a study of a given type should record. A core outcome set specifies the outcomes that studies of a given condition should all measure. Their purpose is to make separate studies comparable, which is something no amount of later analysis can achieve on its own.
Declared interest: Pubrica provides research and medical writing support commercially. Nothing on this page should be read as suggesting that a service can supply data that was never collected. Nor can one make a dataset fit a question it was not built for. Where the required variable is absent, the honest course is to change the question or collect the data.
References and sources
- Benchimol EI, Smeeth L, Guttmann A, Harron K, Moher D, Petersen I, Sørensen HT, von Elm E, Langan SM; RECORD Working Committee. The REporting of studies Conducted using Observational Routinely-collected health Data (RECORD) statement. PLoS Medicine. 2015;12(10):e1001885. doi:10.1371/journal.pmed.1001885 read 20 October 2026 as the version of record deposited in UCL Discovery; the publisher’s own page was unreachable.View the repository record
- Kwok CS, Muntean E-A, Mallen CD, Borovac JA. Data collection theory in healthcare research: the minimum dataset in quantitative studies. Clinics and Practice. 2022;12(6):832–844. doi:10.3390/clinpract12060088 read 20 October 2026. A methodological review proposing a framework; it reports no empirical figures.View the full text
- Sarkies MN, Bowles K-A, Skinner EH, Mitchell D, Haas R, Ho M, Salter K, May K, Markham D, O’Brien L, Plumb S, Haines TP. Data collection methods in health services research: hospital length of stay and discharge destination. Applied Clinical Informatics. 2015;6(1):96–109. doi:10.4338/ACI-2014-10-RA-0097 read 20 October 2026 from two institutional repository records; the publisher’s site is unreachable. Those records disagree on author order, so the ordering above should be confirmed against the publisher. The study reports percent agreement only, with no chance-corrected statistic.View the repository record
- Davidson J, Banerjee A, Muzambi R, Smeeth L, Warren-Gash C. Validity of acute cardiovascular outcome diagnoses recorded in European electronic health records: a systematic review. Clinical Epidemiology. 2020;12:1095–1111. read 20 October 2026 from the DOAJ record. The review covers 81 studies. Its own conclusion is that these diagnoses are generally accurate for research, with named exceptions.View the record and abstract
- Althunian TA, Alrasheed MM, Alnofal FA, Tafish RT, Mira MA, Alroba RA, Kirdas MW, Alshammari TM. Recording type 2 diabetes mellitus in a standardised central Saudi database: a retrospective validation study. BMJ Open. 2023;13:e065468. doi:10.1136/bmjopen-2022-065468 read 20 October 2026.View the full text
- Wurster F, Herrmann C, Beckmann M, Cecon-Stabel N, Dittmer K, Hansen T, Jaschke J, Köberlein-Neu J, Okumu M-R, Pfaff H, Rusniok C, Karbach U. Differences in changes of data completeness after the implementation of an electronic medical record in three surgical departments of a German hospital. BMC Medical Informatics and Decision Making. 2024;24:258. doi:10.1186/s12911-024-02667-0 read 20 October 2026. A separate figure on unsafe recommendations appears in this paper quoted from an earlier study, and is not used here.View the full text
- Albagmi S. Impact of inaccurate clinical coding on financial outcome: a study in a local hospital in Najran, Saudi Arabia. F1000Research. 2024;13:820. doi:10.12688/f1000research.149154.1 read 20 October 2026. A single-site retrospective audit. Its narrative gives the primary-diagnosis error rate inconsistently, so only the abstract figures are quoted here and the agreement statistics are not used.View the full text
- Williamson PR, Altman DG, Bagley H, Barnes KL, Blazeby JM, Brookes ST, Clarke M, Gargon E, Gorst S, Harman N, Kirkham JJ, McNair A, Prinsen CAC, Schmitt J, Terwee CB, Young B. The COMET Handbook: version 1.0. Trials. 2017;18(Suppl 3):280. doi:10.1186/s13063-017-1978-4 read 20 October 2026. Figures the Handbook reports from other reviews are attributed to those reviews rather than to the Handbook.View the full text
- Young AE, Brookes ST, Avery KNL, Davies A, Metcalfe C, Blazeby JM. A systematic review of core outcome set development studies demonstrates difficulties in defining unique outcomes. Journal of Clinical Epidemiology. 2019;115:14–24. doi:10.1016/j.jclinepi.2019.06.016 read 20 October 2026 from the University of Bristol repository. The figure of 5,776 outcomes is this review reporting a finding of Chong et al., not an original result.View the full text
- Hallinan CM, Ward R, Hart GK, Sullivan C, Pratt N, Ng AP, Capurro D, Van Der Vegt A, Liaw S-T, Daly O, Gallego Luxan B, Bunker D, Boyle D. Seamless EMR data access: integrated governance, digital health and the OMOP-CDM. BMJ Health & Care Informatics. 2024;31:e100953. doi:10.1136/bmjhci-2023-100953 read 20 October 2026.View the full text
- World Health Organization. Sharing and reuse of health-related data for research purposes: WHO policy and implementation guidance. Geneva: WHO; 2022. ISBN 978-92-4-004496-8. read 20 October 2026. The landing page was read at WHO; the full text at a mirror whose title, publisher, year and ISBNs match, the WHO file server being unreachable. The policy binds WHO staff and WHO-funded researchers, and is a statement of principle elsewhere.View the publication
- Institute of Medicine (US) Subcommittee on Standardized Collection of Race/Ethnicity Data for Healthcare Quality Improvement; Ulmer C, McFadden B, Nerenz DR, eds. Improving data collection across the health care system. In: Race, Ethnicity, and Language Data: Standardization for Health Care Quality Improvement. Washington DC: National Academies Press; 2009. read 20 October 2026. Its findings concern race, ethnicity and language data in United States hospitals, and are cited here only within that scope.View the chapter
How to cite this article
Pick your referencing style and copy it. Your university or target journal may vary the punctuation — check its guide if it has one.
This article is written to be learned from. Cite it if you are referring to what it says; if you are using the evidence behind it, cite the sources listed above instead.
Work through these before the analysis plan is finalised.
[ ] The research question is written down and fixed
[ ] Each data source identified, with what it was originally collected for
[ ] Population the source actually covers, and who is absent from it
[ ] Every analysis variable confirmed present in the source
[ ] Definition of each variable established, not assumed from its label
[ ] Coding system and version recorded for any coded field
[ ] Validation study sought for any code the conclusion depends on
[ ] Local variation in definitions across sites checked
[ ] Reason for missingness considered for each variable, not just the rate
[ ] Core outcome set checked for the condition before choosing measures
[ ] Minimum dataset checked for the study type
[ ] Linkage method and match rate recorded, if datasets were joined
[ ] Cleaning and exclusion rules written down as they are applied
[ ] Governance and approvals settled before the data move
[ ] Consent basis for reuse established and documented
[ ] Provenance written into the methods section, not a data statement alone
We help you decide what to collect before a study starts, assess whether an existing dataset can answer your question, and report provenance to the standard reviewers expect.